Sagoh
For millions of Americans navigating the complexities of Medicare, the choice between "Traditional Medicare" and "Medicare Advantage" is often framed as a simple preference for delivery style. In reality, that choice can become a permanent, life-altering decision due to a regulatory "coverage trap" that creates a one-way door for millions of beneficiaries.
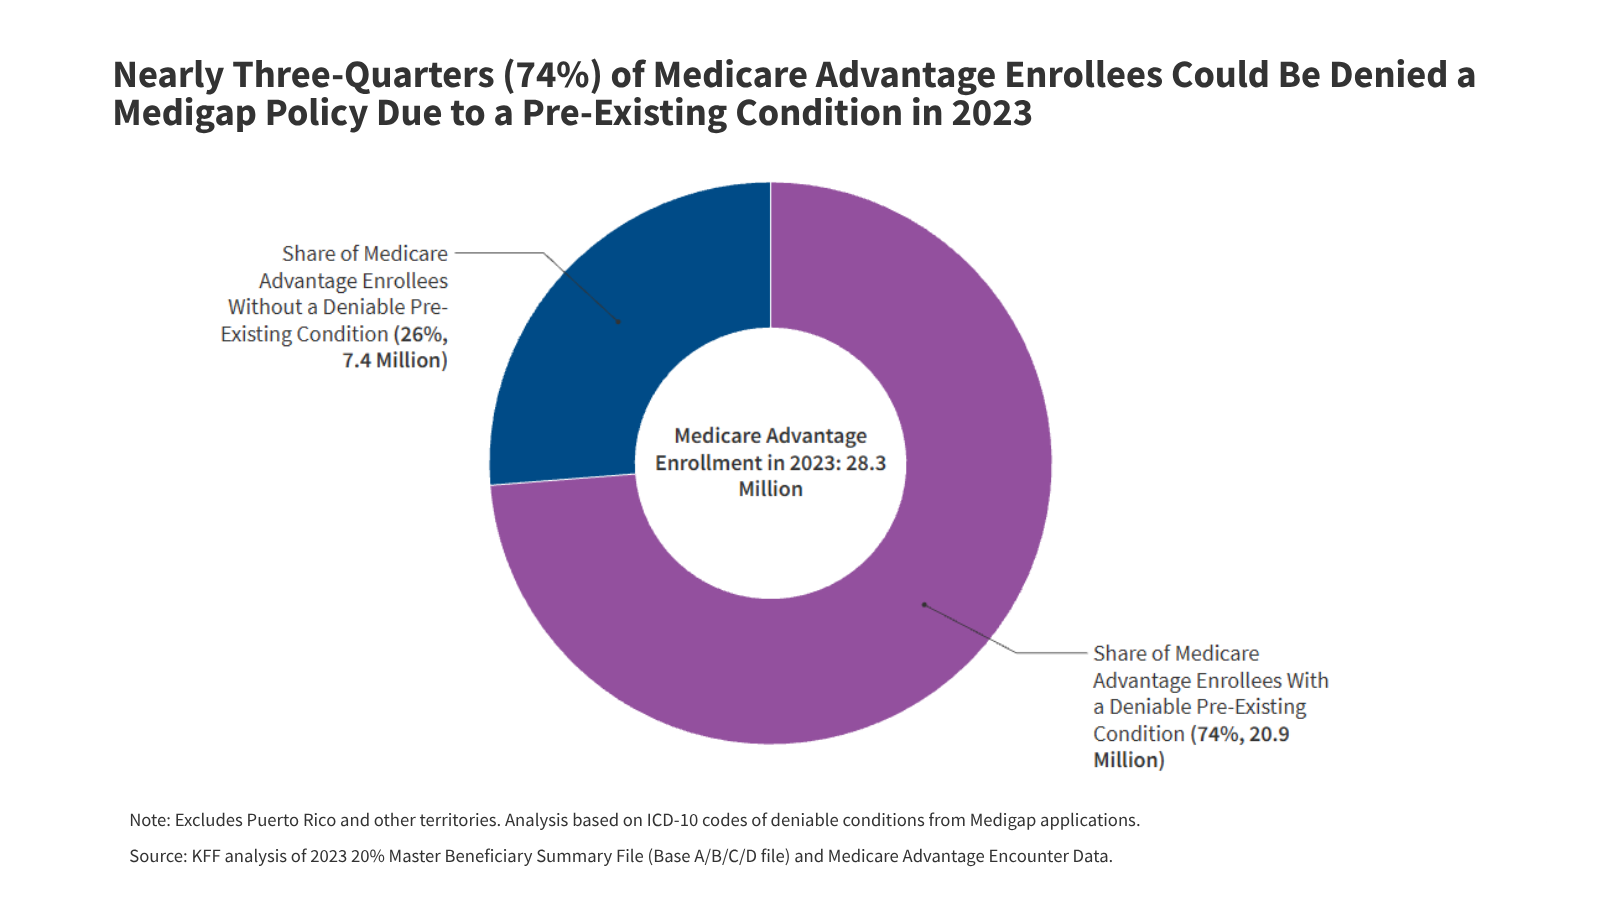
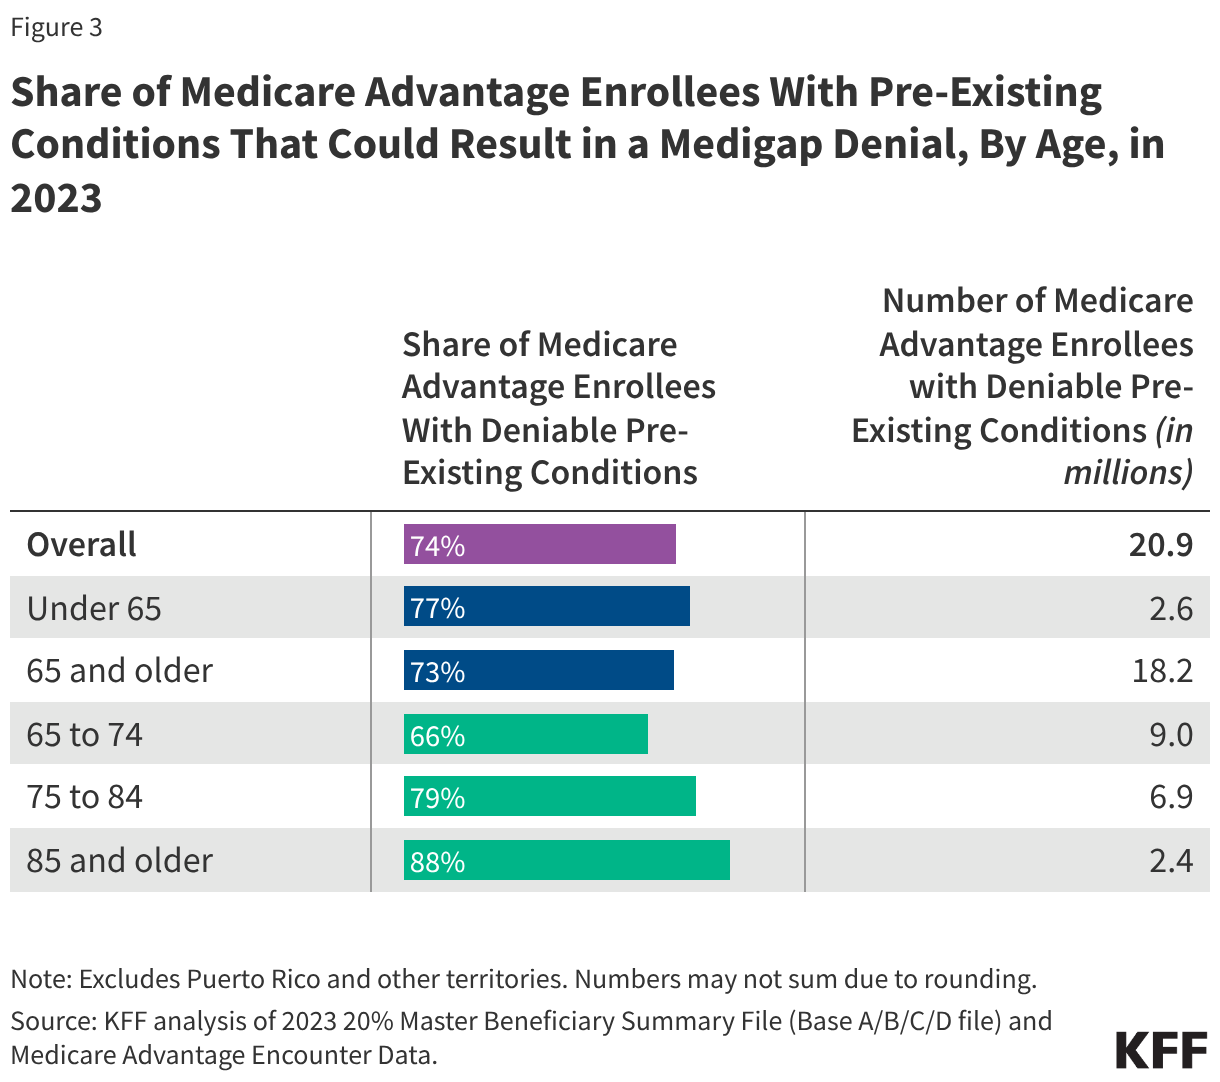
A recent, comprehensive analysis by KFF has shed light on a staggering reality: 74% of Medicare Advantage (MA) enrollees—approximately 20.9 million people—are living with at least one pre-existing condition that could lead to their denial if they attempted to switch to traditional Medicare and purchase supplemental "Medigap" insurance.
The Fundamental Divide: Traditional vs. Advantage
To understand the gravity of this situation, one must understand the structural differences between the two primary ways to receive Medicare benefits.
Traditional Medicare allows beneficiaries to see any doctor or hospital that accepts Medicare, typically without the friction of prior authorizations or restrictive provider networks. However, it comes with significant financial risk. There is no annual out-of-pocket spending cap, leaving beneficiaries exposed to potentially catastrophic medical bills. To mitigate this, most traditional Medicare enrollees purchase Medigap, a private supplemental insurance policy that covers deductibles, copayments, and coinsurance.
Medicare Advantage, by contrast, operates like a private managed care plan. These plans often include lower cost-sharing and an annual out-of-pocket cap, which can be highly attractive to seniors on fixed incomes. The tradeoff, however, is significant: these plans frequently utilize narrow provider networks and require prior authorization for tests, procedures, and specialist referrals.
The problem arises when an enrollee’s health needs change. A beneficiary who chooses Medicare Advantage while healthy may find that, years later, their specific doctor is no longer in-network, or they are struggling to get approvals for necessary treatments. When these enrollees attempt to switch back to traditional Medicare, they discover that without the protection of Medigap, their out-of-pocket costs could become ruinous. And, because of medical underwriting, they are often ineligible to buy a Medigap policy.
A Chronology of Coverage and Enrollment
The current regulatory landscape is defined by a specific, time-sensitive window designed to balance market stability with consumer access.
- The Initial Enrollment Period: When a beneficiary first enrolls in Medicare Part B at age 65, federal law mandates a six-month "open enrollment" window. During this time, private insurers are prohibited from denying a Medigap policy or charging higher premiums based on medical history.
- The "Trial" Period: For those who opt for Medicare Advantage initially, federal law provides a 12-month trial period. If they decide to switch back to traditional Medicare during this first year, they are guaranteed the right to purchase a Medigap policy.
- The Post-Trial Reality: Once those windows close, the regulatory landscape shifts dramatically. Outside of specific state-mandated "guaranteed issue" rules, private insurers are permitted to engage in medical underwriting. They can—and do—deny coverage to applicants based on their health status, effectively locking millions of seniors into their current Medicare Advantage plans.
The Data: A Landscape of Pre-Existing Conditions
The KFF analysis examined 2023 Medicare Advantage encounter data, mapping it against the medical history questions commonly found on Medigap applications. The results provide a sobering look at how widespread these barriers are.
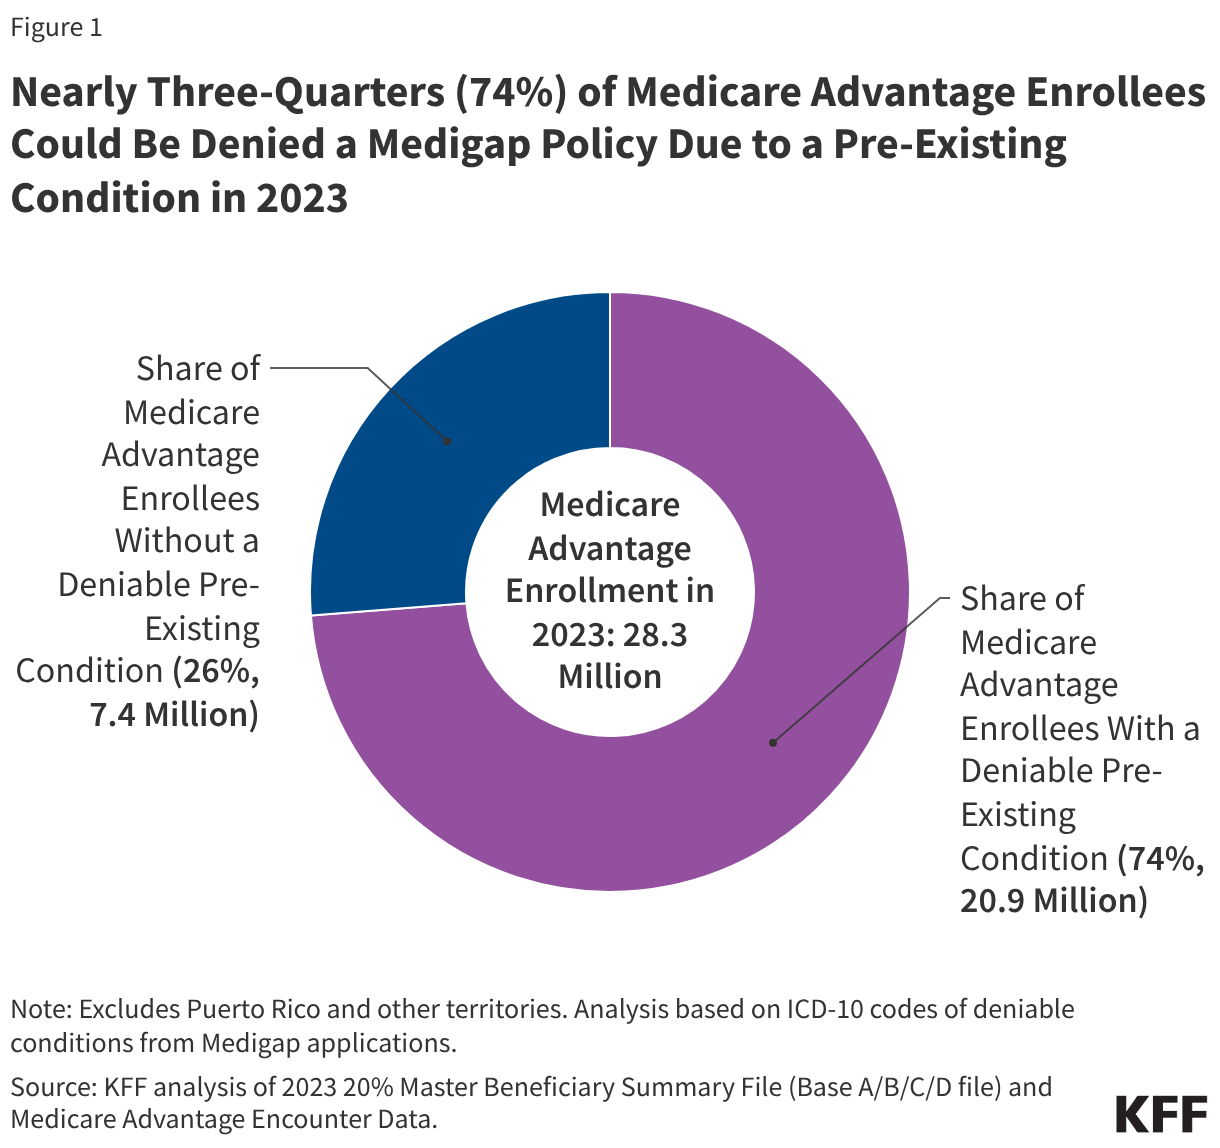
Nearly three-quarters (74%) of full-year Medicare Advantage enrollees have at least one condition that could trigger a denial. The prevalence of these conditions is not just a matter of age; it is a systemic issue inherent to the population that relies on Medicare.
Prevalence of "Deniable" Conditions
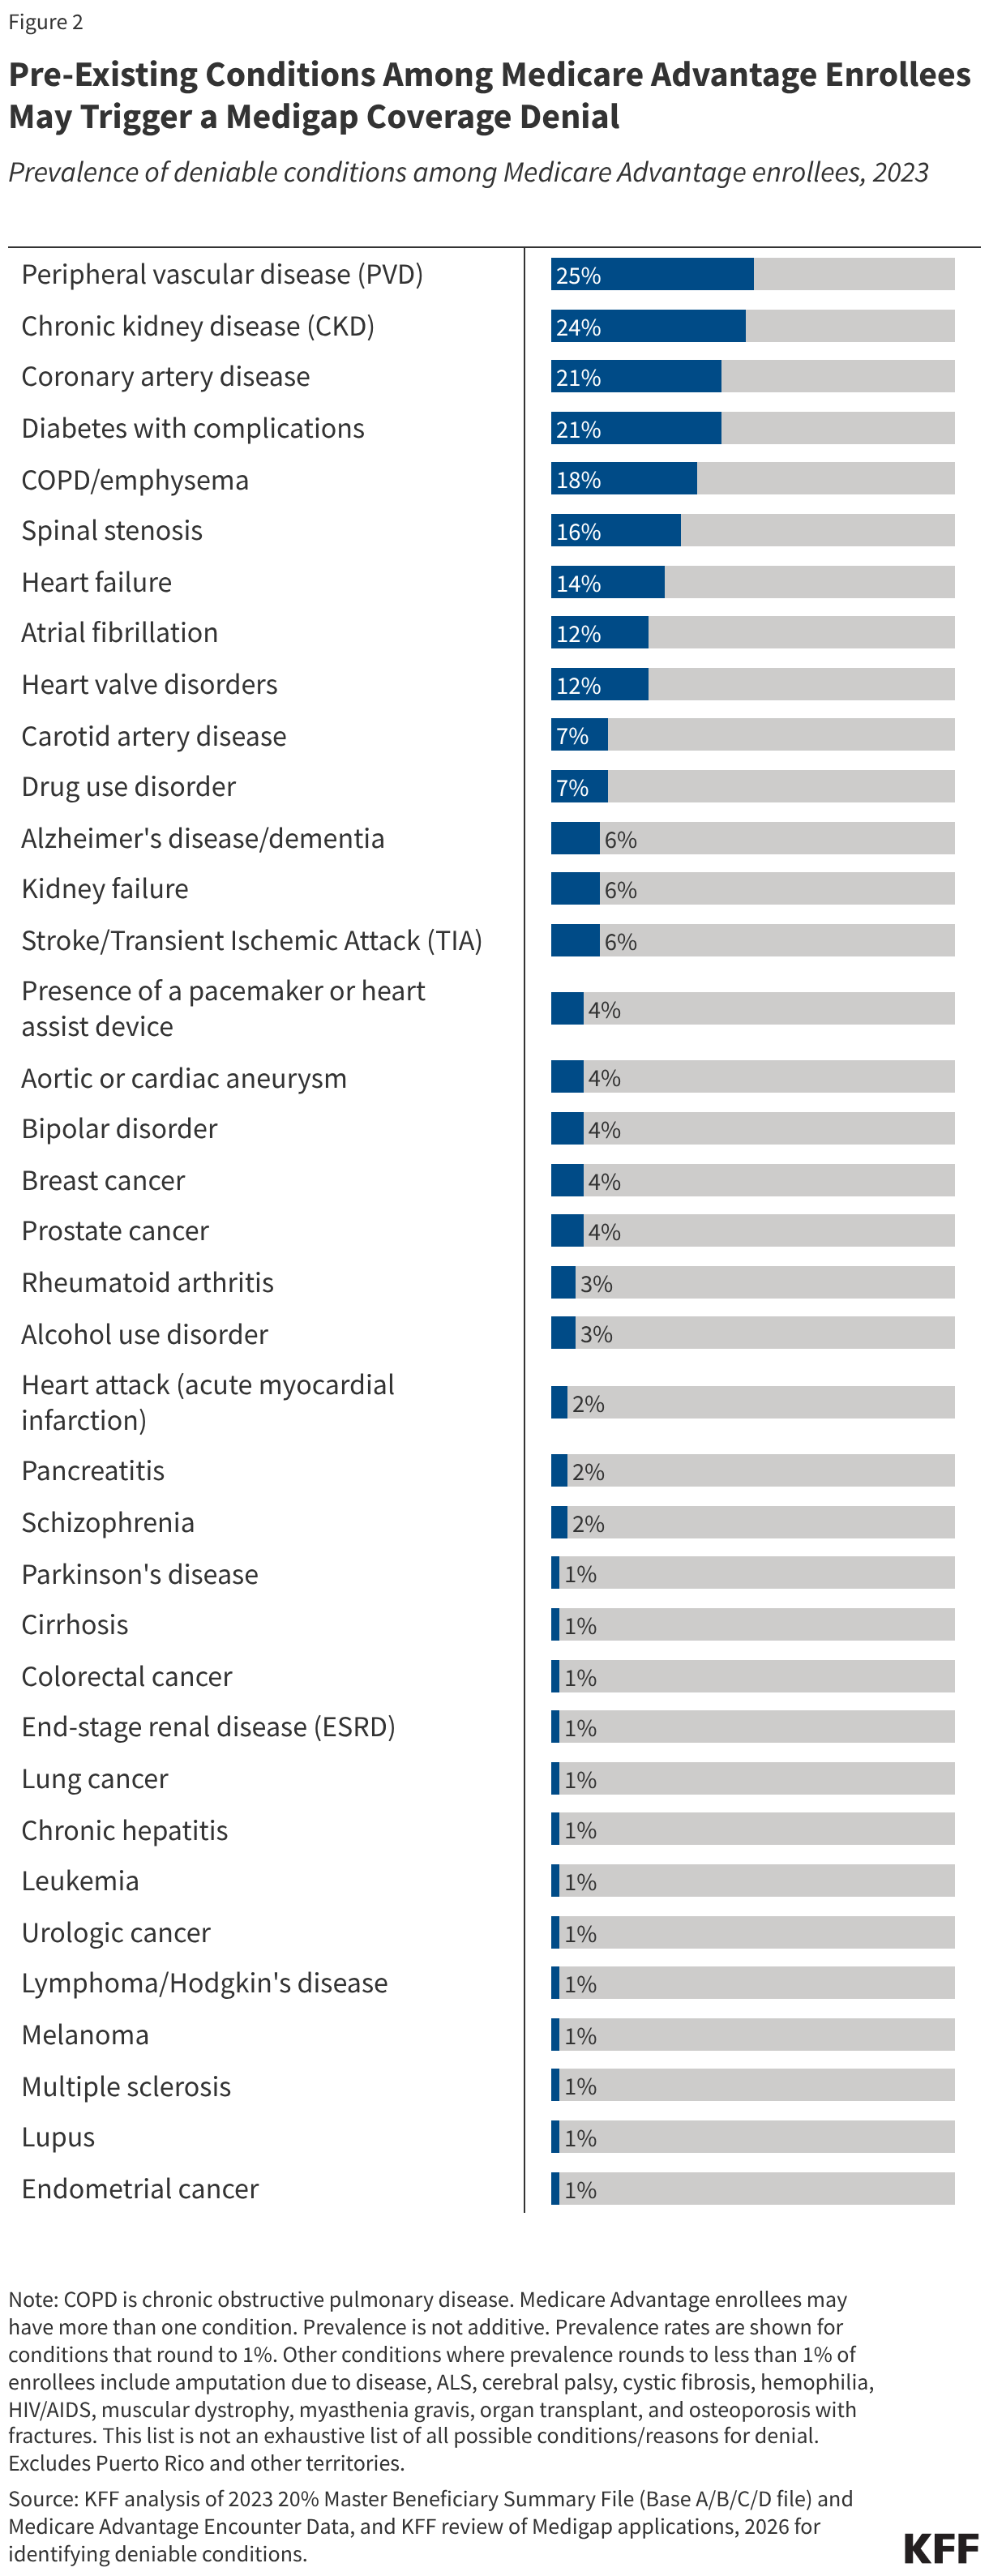
The analysis identified several chronic conditions that are highly prevalent among the MA population. At least one in five enrollees is diagnosed with:
- Peripheral Vascular Disease: 25%
- Chronic Kidney Disease: 24%
- Coronary Artery Disease: 21%
- Diabetes with complications: 21%
Beyond these, a host of other conditions—including atrial fibrillation, heart failure, chronic obstructive pulmonary disease (COPD), multiple sclerosis, and various cancers—frequently appear on the "exclusion lists" of private Medigap carriers.
The "Coding Intensity" Paradox
An ironic element of this crisis is the role of Medicare Advantage payment models. Because MA plans are paid based on the risk-adjustment of their enrollees, they have a strong financial incentive to document every possible diagnosis code for their members. This practice, known as "coding intensity," means that a condition might be documented in an MA enrollee’s record that might never have been officially noted in a traditional Medicare claim file. Consequently, the very system that encourages aggressive documentation of health issues may be inadvertently disqualifying those same individuals from leaving the system.
Regional and Demographic Variations
The barriers to switching are not distributed equally across the United States.
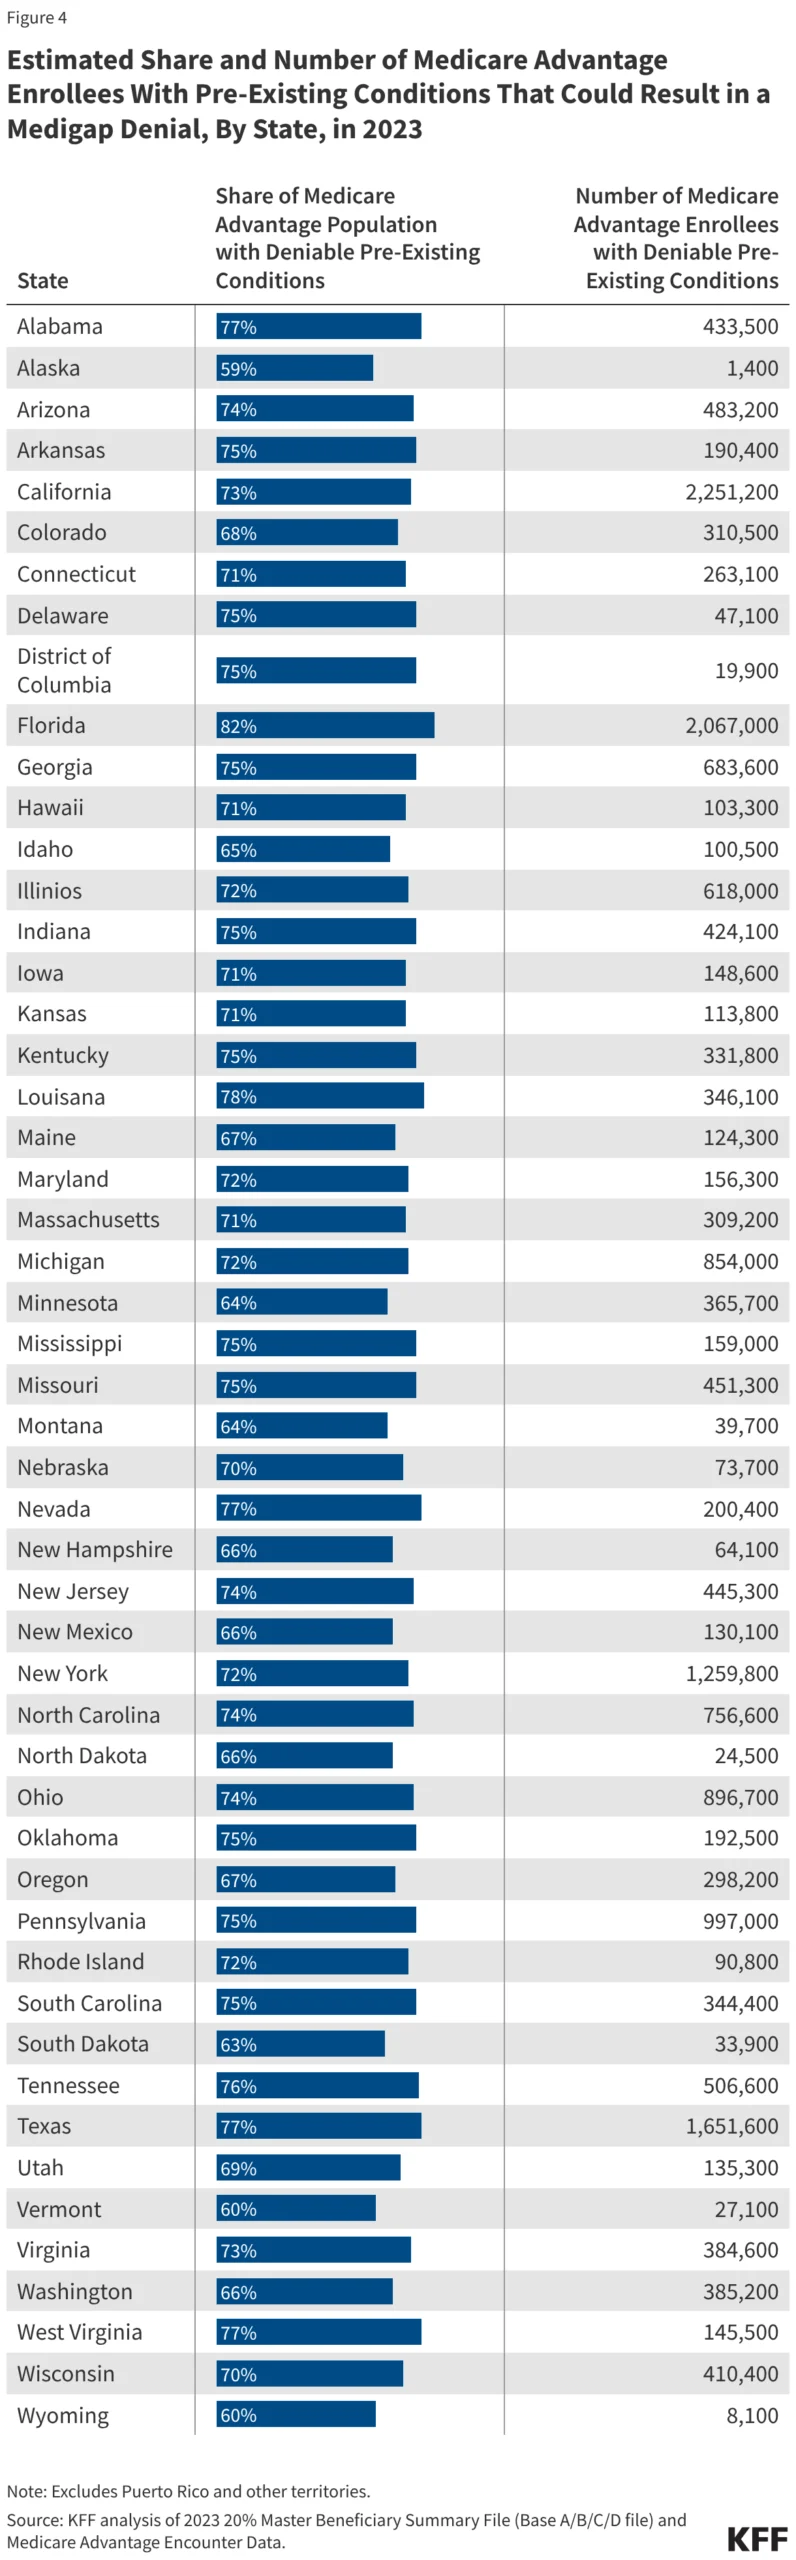
- State-Level Disparities: In Florida, 82% of MA enrollees have a condition that could lead to a Medigap denial. Conversely, states like Vermont, Wyoming, and Alaska see lower, though still significant, rates (between 59% and 60%).
- Age and Disability: Interestingly, the share of beneficiaries under age 65 with deniable conditions is higher than those aged 65–74 (77% vs 66%). This is largely because the under-65 population is comprised of individuals who qualified for Medicare due to long-term disabilities, many of which are specifically targeted by medical underwriting. As beneficiaries age into their 80s, the likelihood of having a deniable condition rises to 88%, creating a "health cliff" where the need for stable, predictable coverage is highest, but the ability to secure it is at its lowest.
Implications: The Need for Policy Reform
The current system creates a significant "lock-in" effect. By forcing beneficiaries to choose between the managed care of Medicare Advantage and the potential cost-exposure of traditional Medicare, regulators have created a market where mobility is severely restricted.
The Argument for Protection
Proponents of the status quo argue that the current underwriting rules are necessary to prevent "adverse selection." If people were allowed to switch to traditional Medicare and buy Medigap only when they became seriously ill, the risk pool for Medigap would become skewed, causing premiums to skyrocket for everyone. The current six-month open enrollment period is intended to force both healthy and sick individuals into the pool at the same time, keeping premiums stable.
The Case for Change
Critics argue that the system is fundamentally unfair to those who did not anticipate the limitations of their Medicare Advantage plans. When a patient develops a chronic condition, they often find that the "advantages" of their plan—such as low monthly premiums—are outweighed by the "hidden costs" of prior authorization delays, limited networks, and restricted access to top-tier specialists.
The disparate rules across states also create a "zip-code lottery." In states like New York, Massachusetts, Connecticut, and Maine, insurers are required to offer Medigap policies regardless of health history. In these states, the "lock-in" effect is significantly mitigated. Advocacy groups are increasingly calling for federal standards that would grant all seniors periodic, guaranteed-issue opportunities to switch to traditional Medicare without the fear of medical underwriting.
Conclusion: A System at a Crossroads
The KFF analysis serves as a critical reminder that for the American senior, health insurance is not a static product. As health needs evolve, the ability to pivot coverage is essential. However, the current intersection of Medicare Advantage and Medigap underwriting creates a precarious environment where the most vulnerable—those with chronic, complex health conditions—are the most restricted in their ability to seek the care model that best serves them.
As the population continues to age and the enrollment in Medicare Advantage reaches record highs, the debate over portability and consumer protection will likely intensify. Without federal intervention to harmonize guaranteed-issue rights, millions of Americans will remain tethered to plans that may no longer suit their medical realities, highlighting a significant gap in the promise of universal access to Medicare.


 Lina Hope