



 Muslim
By Nicole Lou, Senior Staff Writer, MedPage Today
October 13, 2026
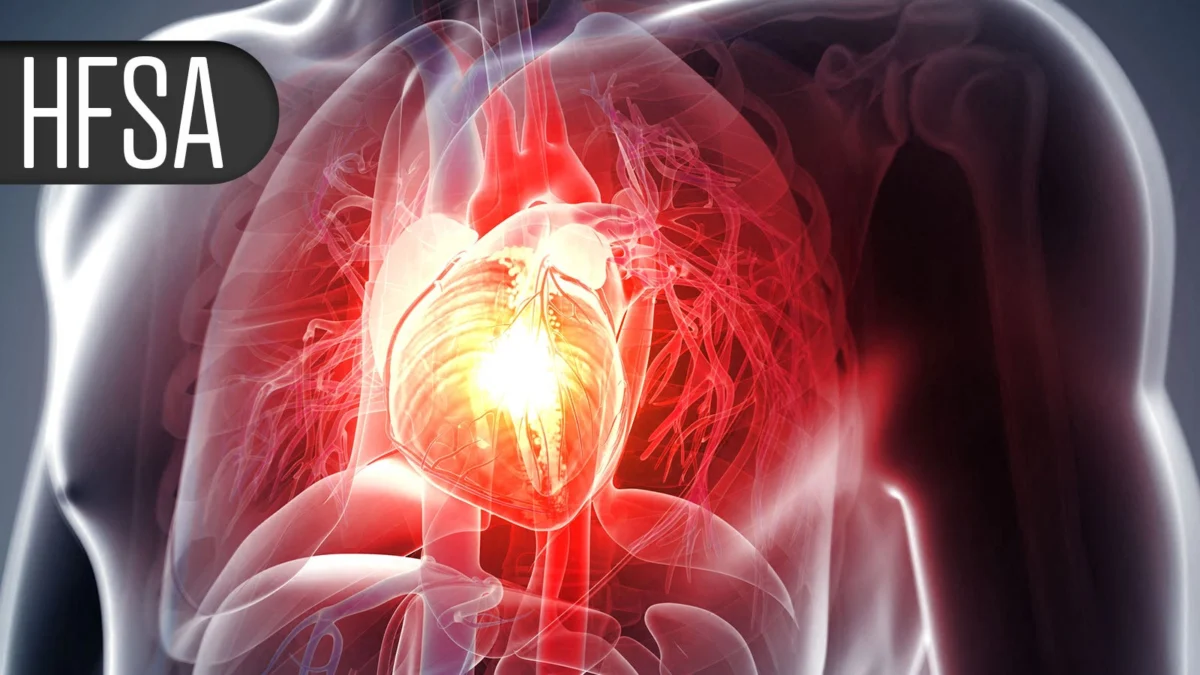
In the rapidly evolving landscape of heart failure (HF) management, few emerging technologies have generated as much curiosity—and healthy skepticism—as Cardiac Microcurrent (C-MIC) therapy. As researchers gathered at the Heart Failure Society of America (HFSA) annual meeting in Phoenix this October, the mood was one of cautious excitement. Early-stage clinical data suggests that C-MIC may offer a transformative approach to treating refractory heart failure, with results so robust that even the lead investigators describe them as “almost too good to be true.”
As the medical community seeks alternatives for patients who have exhausted traditional pharmaceutical and device-based interventions, C-MIC stands at a critical juncture. The shift from invasive surgical epicardial implants to a less-daunting subcutaneous approach marks a potential turning point in the therapy’s viability for a broader, sicker population.
The Core Concept: Rewiring the Myocardium
At its physiological foundation, C-MIC therapy is designed to address the electrical and structural degradation of the heart. Researchers have long noted that myocardial electrical fields are altered during the progression of heart failure. These alterations are closely associated with myocardial edema—the swelling of heart tissue—which often serves as a substrate for left ventricular dysfunction.
The hypothesis behind C-MIC is elegant: by introducing precise microcurrents, the therapy aims to shift activated fibroblasts, the cells responsible for scarring and structural stiffness, toward a less fibrogenic state. By reducing this myocardial stiffness and recalibrating the electrical environment, the therapy seeks to improve ventricular structure and, by extension, the heart’s overall pumping capacity.
Chronology of Development: From C-MIC I to IV
The evolution of the C-MIC platform has been marked by a transition from experimental surgery to refined, patient-centered technology.
C-MIC I & II: The Surgical Foundation
The initial iteration of the therapy required an epicardial implant, a surgical procedure that, while effective, posed significant risks and logistical hurdles. The C-MIC II trial was a milestone, focusing on patients with refractory, non-ischemic heart failure with reduced ejection fraction (HFrEF).
In a cohort of 65 randomized patients, the surgical implant was associated with marked improvements in Left Ventricular Ejection Fraction (LVEF), symptom management, functional capacity, and overall quality of life. However, the trial was not without limitations. It relied on an open-label design and site-reported cardiopulmonary exercise test (CPET) values, which raised concerns regarding potential bias and heterogeneous data acquisition.
C-MIC III: The Subcutaneous Pivot
Recognizing the limitations of surgical access, developers pivoted to a subcutaneous approach. As reported by Stefan Simovic, MD, of the University of Kragujevac in Serbia, the subcutaneous system allows for a far less invasive procedure. Performed in the cardiac catheterization lab under moderate sedation, the generator and leads are placed subcutaneously, with position verified via fluoroscopy. This innovation drastically lowers the barrier to entry, potentially making the therapy accessible to a much sicker patient demographic.
The Road Ahead: C-MIC IV
The upcoming C-MIC IV trial represents the most rigorous test yet. Moving toward a sham-controlled, crossover design, the study aims to enroll 60 patients with LVEF ranging from 20% to 40%. Crucially, this trial expands the inclusion criteria to encompass both ischemic and non-ischemic HF, addressing a significant gap in previous research.
Supporting Data: Validating the "Incredible" Results
The recent data presented at the HFSA meeting served as a necessary "gut check" for the C-MIC program. A post-hoc analysis of the C-MIC II trial, utilizing a blinded core lab to re-evaluate CPET findings, sought to determine if the original claims of efficacy held up under scrutiny.
CPET Re-analysis
The re-analysis included 42 patients (mean age 62; 70% male; mean LVEF 30%). Dragana Kosevic, MD, of the Cardiovascular Institute Dedinje, reported that weight-adjusted peak VO2 improved with a +2.70 mL/min/kg change.
"Objective CPET findings support the functional benefits observed in C-MIC II," Kosevic stated during the session. However, she acknowledged the magnitude of the improvement, noting, "Yes, it is too good to be true, to be honest. That’s why we need more. We need larger randomized studies and more centers involved."
Comparing Subcutaneous to Surgical
In a comparative analysis presented by Dr. Simovic, 10 patients who received the subcutaneous C-MIC III implant were compared against 10 patients with the surgical C-MIC II implant and 10 matched controls. The findings were striking: the subcutaneous group showed comparable improvements in LVEF, 6-minute walking distance, and KCCQ quality-of-life scores.
While the sample sizes remain small—a limitation that cannot be overstated—the trend suggests that the subcutaneous delivery method does not compromise the therapeutic efficacy observed in the more invasive surgical predecessors.
Official Responses and Expert Skepticism
The medical community’s reaction to the C-MIC data has been a mixture of cautious optimism and professional skepticism. During the HFSA session, John Teerlink, MD, of the San Francisco Veterans Affairs Health Care System and UCSF Medical Center, acted as a discussant.
Dr. Teerlink did not mince words regarding the reported magnitude of benefit. "I am highly skeptical of the magnitude of the benefit that you folks are showing, but I remain actually very enthusiastic about moving this forward," Teerlink remarked. His skepticism centers on the dramatic improvements in peak VO2, which often defy the typical trajectories seen in device-based heart failure trials.
The research team, to their credit, has embraced this skepticism. By shifting to a sham-controlled model for the C-MIC IV trial, they are attempting to isolate the true therapeutic effect from the placebo effect that can often cloud surgical intervention outcomes.
Implications for Clinical Practice and Safety
The future of C-MIC hinges on its safety profile and its ability to integrate with existing medical hardware.
The Question of Interference
A primary concern raised by experts is the interaction between C-MIC and the "crowded" environment of a heart failure patient’s chest. Many of these patients already possess implantable cardioverter-defibrillators (ICDs), cardiac resynchronization therapy (CRT) devices, or coronary stents.
"If somebody has coronary stents, do you actually electrically induce currents in those with this microcurrent probe?" Dr. Teerlink asked. Dr. Simovic admitted that the data on electromagnetic interference remains a significant "known unknown." "We are afraid of interference, especially with the ICD lead," he acknowledged. Determining the compatibility of C-MIC with standard-of-care cardiac devices will be a prerequisite for any broad clinical adoption.
Infection Risks
While the move to a subcutaneous approach has reduced surgical complexity, it has not eliminated risk. Dr. Simovic reported one instance of infection in the C-MIC III cohort. However, he noted that the subcutaneous system offers a distinct advantage in terms of management: "Looking from the empirical point of view… the explanation of the system was much easier."
Conclusion: The Need for Rigor
Cardiac microcurrent therapy currently occupies the space between a groundbreaking medical discovery and an unproven experimental procedure. The +2.70 mL/min/kg improvement in peak VO2 and the 30-point jump in KCCQ scores are statistically impressive, but as the field of cardiology has learned time and again, small-scale, open-label trials are notoriously prone to overestimating effect sizes.
The transition to the C-MIC IV sham-controlled trial is the correct, and perhaps only, path forward. If the results hold under the scrutiny of a rigorous, blinded, and randomized environment, C-MIC could provide a much-needed lifeline for patients for whom current therapies are insufficient.
For now, the mantra of the research team—and the verdict of the broader cardiology community—is clear: The data is intriguing, the technology is innovative, but the burden of proof remains high. The next two years of study will determine whether C-MIC is truly the next great leap in heart failure management or simply an artifact of small-sample optimism.


 Nila Kartika Wati
 Neng Nana






