


 Sagoh
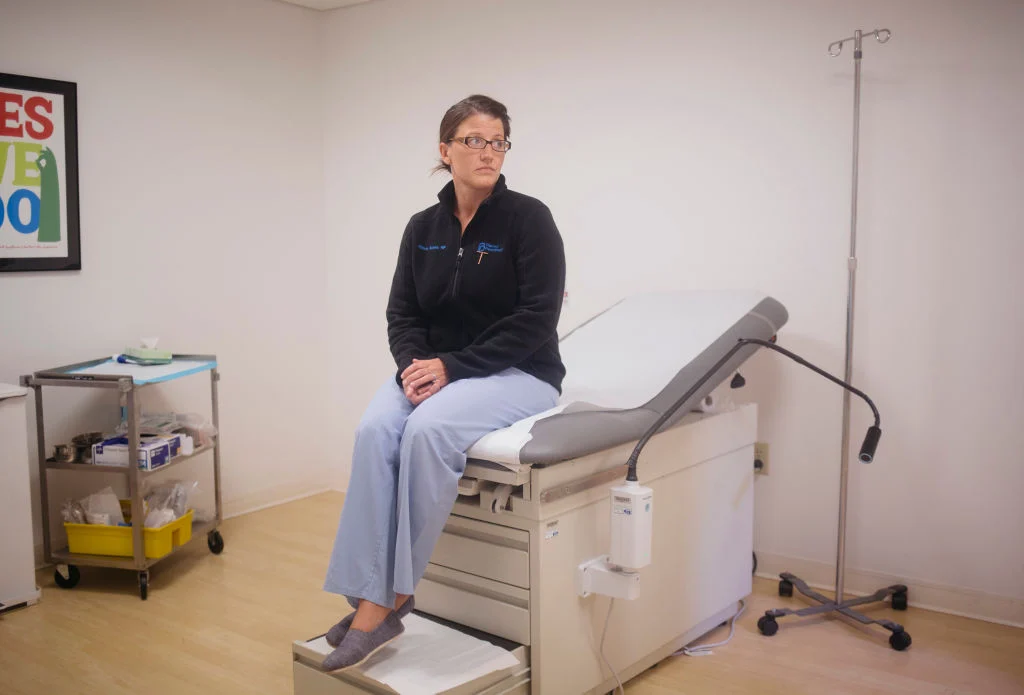
In the wake of the Supreme Court’s 2022 decision to overturn Roe v. Wade, the national conversation surrounding abortion has remained hyper-focused on the morality and legality of the procedure itself. However, a new, investigative work by veteran healthcare reporter Alice Miranda Ollstein suggests that the seismic shift in American jurisprudence has triggered a far more profound, systemic crisis. In her new book, Side Effects: How Abortion Bans Impact Everyone’s Health (The New Press, Oct. 27), Ollstein argues that the legal and regulatory fallout from these bans is not merely restricting reproductive care; it is actively dismantling the foundations of general medicine.
From the shuttering of essential clinics to the chilling of life-saving clinical trials, the medical landscape in the United States is being reshaped in ways that affect patients with no connection to abortion services—including men, children, and those battling chronic diseases like cancer and autoimmune disorders.
The Domino Effect on General Healthcare Access
The premise of Side Effects is that medical care is not a siloed industry. When the law intervenes in one facet of reproductive medicine, it inevitably destabilizes the surrounding ecosystem. Ollstein notes that the impacts are multifaceted, determined by geography, patient demographics, and the specific nature of their medical needs.

Perhaps most concerning is the physician exodus currently underway. In states with draconian abortion bans, doctors report feeling unable to practice medicine ethically or legally. This is not limited to OB-GYNs; the fear of litigation is driving medical professionals across specialties to flee these regions. The result is a widening "healthcare desert," where basic access to primary care, emergency services, and chronic disease management is becoming increasingly precarious for the entire population, regardless of gender or reproductive status.
A Chronology of Regulatory Encroachment
The erosion of healthcare access did not happen overnight; it is the culmination of decades of strategic legal maneuvering that has gained unprecedented momentum in the last two years.
- Pre-2022: The groundwork for "fetal personhood" and the targeting of specific medications like mifepristone began long before the fall of Roe. Anti-abortion advocates focused on the Comstock Act and the classification of reproductive drugs as controlled substances.
- June 2022: The Dobbs v. Jackson Women’s Health Organization ruling removed federal protections for abortion, allowing states to enact total or near-total bans.
- 2023-2024: States began implementing aggressive regulations, such as Louisiana’s reclassification of mifepristone and misoprostol as controlled substances. This shift fundamentally altered hospital emergency protocols, forcing life-saving drugs into locked, secure storage, which adds critical, potentially fatal minutes to emergency care for postpartum hemorrhaging.
- Early 2024: The Alabama Supreme Court’s ruling on IVF embryos signaled a new phase of the crisis, applying "fetal personhood" to cryopreserved embryos. While temporary legislative patches were enacted following public outcry, the underlying legal theories remain active threats to fertility services nationwide.
Supporting Data: The Pharmacological Chokepoint
One of the most alarming revelations in Ollstein’s reporting is the impact of "blanket refusals" at pharmacy counters. Methotrexate, a gold-standard medication for lupus, rheumatoid arthritis, and various cancers, is also used to manage ectopic pregnancies. Because of this dual-use, many pharmacists and retail chains have implemented preemptive refusals to fill prescriptions for patients who are of reproductive age, out of fear that they could be held liable for an "illegal abortion."

This phenomenon extends to teratogenic drugs—medications that can cause birth defects—used for epilepsy, hypertension, and heart conditions. The resulting medical "chilling effect" means that individuals who are not even pregnant, or who are biologically incapable of pregnancy, are being denied standard, life-saving care. The legal anxiety has effectively replaced medical judgment, forcing patients to navigate a gauntlet of administrative hurdles just to receive their routine, non-reproductive prescriptions.
Official Responses and the "Comstock" Threat
The potential enforcement of the Comstock Act of 1873 looms over the future of American healthcare. The act, which prohibits the mailing of "articles" intended for abortion, is being viewed by some legal strategists as a potential federal tool to block the distribution of all abortion-related supplies.
Ollstein highlights that the literal application of this 19th-century law would be catastrophic for the medical supply chain. Hospitals rely on the mail and private couriers to deliver surgical instruments, gloves, specimen kits, and various pharmaceuticals. If anti-abortion organizations successfully use the Comstock Act to trigger federal investigations or "sting" operations, the result would be a massive, systemic paralysis of medical supply logistics. While mass mail inspections are logistically impossible, the threat of selective, aggressive prosecution is already being used to intimidate providers and manufacturers into self-censorship and supply-chain withdrawal.

Implications: The Death of Scientific Progress
Perhaps the most insidious long-term consequence of these bans is the "data vacuum" they are creating. Clinical trials are the engine of medical innovation, yet they are increasingly impossible to conduct in states with abortion restrictions.
International research ethics standards require that participants in clinical trials have access to comprehensive reproductive care, including the right to terminate a pregnancy if an experimental drug causes severe fetal malformation or endangers the patient. When states ban this care, they effectively bar their residents from participating in the development of new therapeutics.
Ollstein cites the example of Gulf War Illness research. Mifepristone, often vilified as merely an "abortion pill," has shown promise in treating this debilitating condition in male veterans. Because of the political toxicity surrounding the drug, researchers are finding their funding pulled, their institutional review boards (IRBs) blocking their protocols, and their work stifled by the mere association with abortion. When studies exclude pregnant people—or women of childbearing potential entirely—the resulting data is incomplete, leading to medical guidelines that are poorly suited for the population at large.

Looking Toward the Future
The situation in America is, as Ollstein describes it, a systemic crisis where "legal restrictions on reproductive healthcare ripple outwards, compromising the health and safety of all patients." The "side effects" of the current legal climate are not limited to the intended targets of these laws. They are felt by the cancer patient waiting for chemotherapy, the veteran struggling with chronic illness, the woman seeking to build a family through IVF, and the physician trying to provide standard care without the fear of a prison sentence.
As states continue to test the limits of these restrictions, the U.S. healthcare system faces a fork in the road. Will it continue to succumb to a climate of fear and legal obfuscation, or will the medical community and the public successfully push back against the intrusion of political ideology into the examination room?
The evidence presented in Side Effects suggests that the cost of inaction is too high. The loss of medical infrastructure, the decline in research quality, and the erosion of patient-provider trust are not minor inconveniences; they are markers of a declining standard of care. As the debate over reproductive rights moves forward, it must contend with the reality that, in the world of medicine, everything is connected. When we limit the care one group can receive, we eventually limit the care available to everyone.

For those looking to understand the full scope of this transformation, Ollstein’s work serves as a sobering, essential roadmap of what is at stake for the American patient. The question remains: how much of the nation’s medical progress are we willing to sacrifice at the altar of political gain?


 Reynand Wu

 Jia Lissa






